


At a glance

Overview
Telehealth and telemedicine existed long before the COVID-19 pandemic, but health systems' use of telehealth changed significantly starting in March 2020.1
Growing interest in telehealth services and easier access to them, coupled with widespread cardiovascular disease (CVD) risk factors in the U.S., indicated a need to rapidly produce evidence-based telehealth interventions focused on high blood pressure.23
Although telehealth is not a one-size-fits-all solution, both FQHCs evaluated wanted to continue offering telehealth services and reported that their patients did as well (Figure 1).
Evaluation purpose and methods
After receiving nominations from health systems around the country, DHDSP selected ARcare Augusta and Terros Health—two FQHCs—to participate in rapid evaluations in 2020.
The rapid evaluations documented early telehealth implementation, outcomes, and impact on access to care using a mixed-methods approach. Data sources included documents, interviews, and electronic health record (EHR) data.

Key findings and lessons learned include:
- Staff, training, and leadership support are key drivers for telehealth implementation.
- Telehealth both addresses patients' needs and poses new barriers to care.
- Telehealth is not a one-size-fits-all solution.
- Health systems and their patients want access to telehealth services long term.
Evaluation findings: ARcare Augusta
Overview
ARcare is a FQHC headquartered in Augusta, Arkansas that provides primary care, chronic disease management, behavioral health, and pediatric services at 48 clinics. Within its network, 17 clinics serve rural, medically underserved counties in Arkansas, Kentucky, and Mississippi.
Telehealth implementation
ARcare began providing telehealth in 2018, using technology to connect clinicians with patients at satellite clinical or community sites. In March 2020, at the start of the COVID-19 pandemic, ARcare rapidly expanded its telehealth services to meet patients' needs and to improve access to care.
From March 2019 – February 2020, there were 9,904 encounters among patients with high blood pressure or high cholesterol, of which 5% (n=489) occurred via telehealth.
Following telehealth expansion, from March 2020 to March 2021, there were a total of 9,086 encounters of which 30% (n=2683) occurred via telehealth. The proportion of telehealth visits peaked in April 2020 (60%) and remained greater than 18% of all monthly visits through March 2021 (Figure 2).
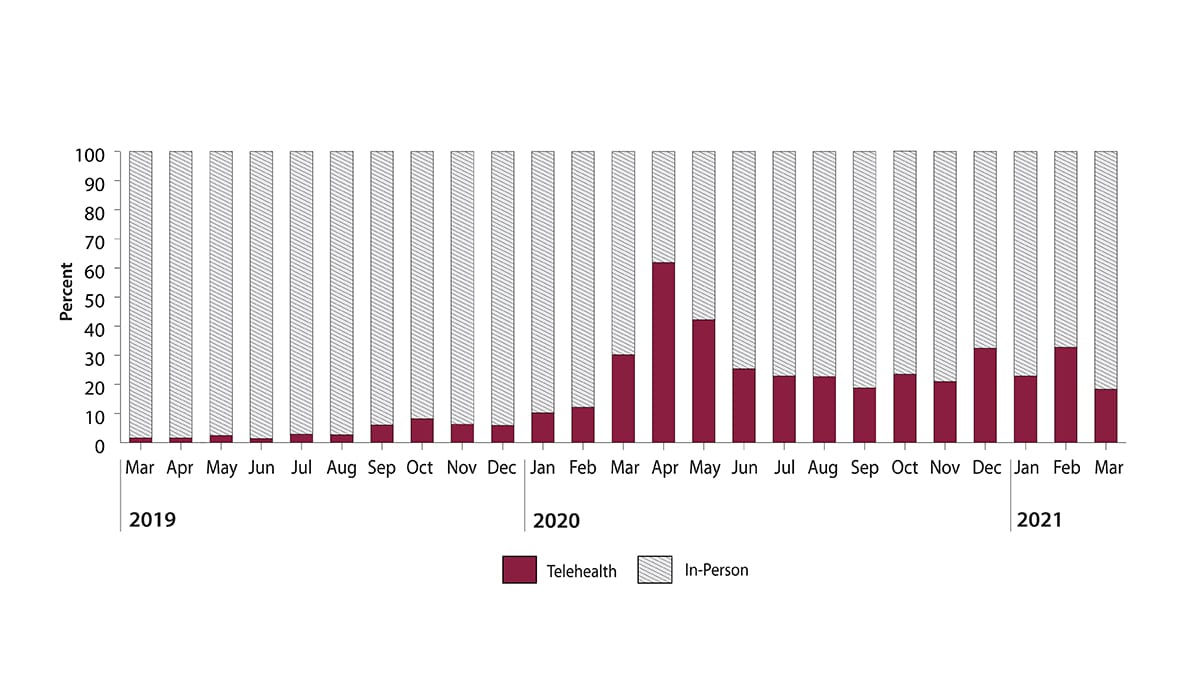
View HTML alternative description of this bar chart.
Access to care via telehealth and blood pressure control
Barriers: ARcare staff observed that older adult patients were more resistant to using telehealth or lacked the necessary skills to use telehealth technologies. Some patients also faced barriers to telehealth because of unreliable broadband internet access in rural areas.
Facilitators: ARcare staff perceived that telehealth reduced no-show rates, increased medication adherence, and increased patient reach. Health care professionals also perceived that telehealth helped some patients overcome transportation barriers that had previously limited their access to health care.
The evaluation assessed aggregate changes in blood pressure control rates among patients with a diagnosis of high blood pressure who sought telehealth services during March 2019 and March 2021.
There were no statistically significant differences in blood pressure control between the baseline period (53.4%, March 2019–February 2020) and following the rapid expansion of telehealth services during the COVID-19 pandemic (57.4%, March 2020–March 2021) (p=0.31).
This finding suggests that blood pressure control rates remained relatively consistent during these time periods and that telehealth may be a suitable strategy for meeting the needs of Arcare patients with high blood pressure.
Evaluation findings: Terros Health
Health overview
Terros Health is headquartered in Maricopa County, Arizona, and provides primary care, chronic disease management, and trauma-informed behavioral health services. They have 13 locations, including four FQHCs.
Telehealth implementation
Prior to March 2020, Terros Health exclusively provided in-person health care services through their four FQHC primary care clinics. In March 2020, at the start of the COVID-19 pandemic, Terros rapidly adopted telehealth services to continue providing health care while minimizing in-person visits.
From March 2019 to August 2021, there were 10,287 clinic visits; 58.9% (n= 6,063) occurred in person and 41.0% (n=4,224) occurred by telehealth using video call or telephone.
The proportion of patients with a telehealth visit increased to 36.8% in March 2020 and peaked at 89.1% in July 2020. Telehealth accounted for 35.0% to 70.0% of visits during August 2020 and August 2021 (Figure 3).
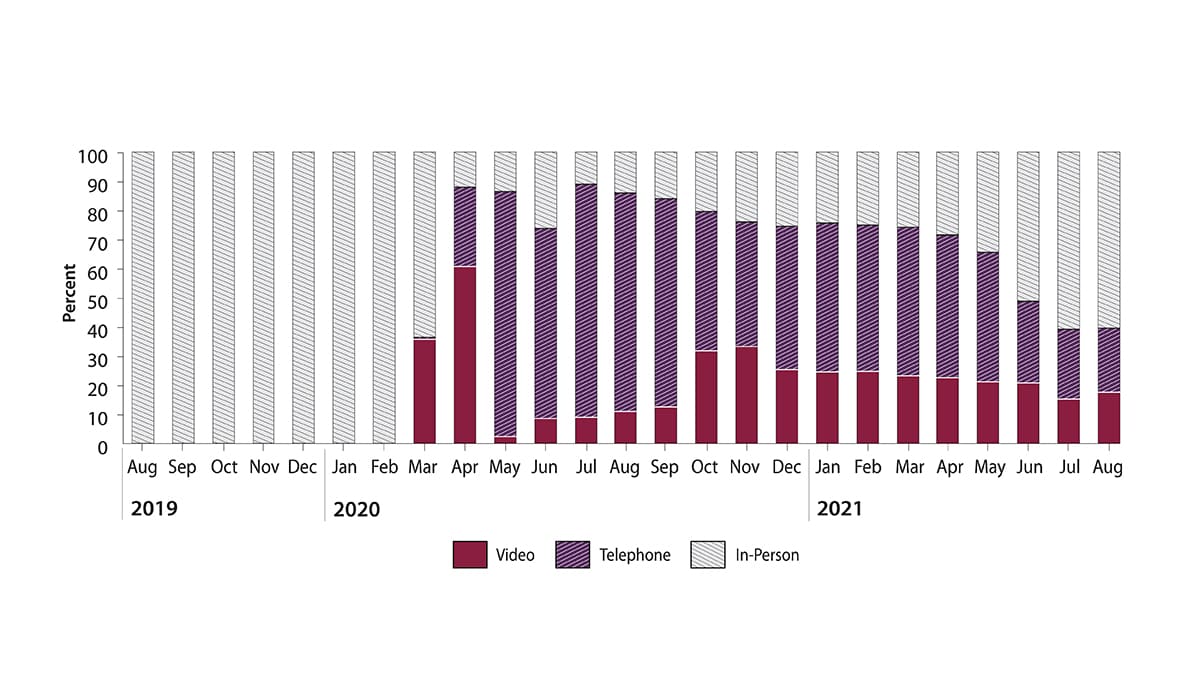
View HTML alternative description of this bar chart.
Access to care via telehealth and blood pressure measurement
Barriers: Terros staff and health care professionals perceived that broadband internet access, homelessness, and patient-preferred language were barriers for patients accessing care through telehealth. Terros staff also reported differences in telehealth adoption according to patients' race and ethnicity.
Facilitators: Terros staff perceived that telehealth reduced no-show rates, allowed patients to continue health care, and helped patients continue taking their medicines during the pandemic. Telehealth visits also increased the number of people using health care services, specifically among patients who could not take time off work or needed to find childcare coverage for an in-person appointment. Additionally, Terros Health staff and health care professionals perceived that telehealth helped patients overcome transportation barriers that limited access to in-person health care.
There were a substantial number of missing blood pressure readings overall (39.4%, n = 4,062), differing significantly by type of clinic visit (p < 0.001)—in-person, video call, or telephone. From March 2019 to August 2021, more than 85% of blood pressure readings were missing for all telehealth visits, while only 8% of blood pressure readings were missing for in-person visits. This indicates that telehealth may present challenges for consistently recording blood pressure in a virtual setting.
Related resources
The Pharmacists' Patient Care Process Approach Guide: The guide is to engage pharmacists in patient hypertension management through the Pharmacists' Patient Care Process (PPCP).
Team-Based Care to Improve Blood Pressure Control: Public health practitioners and state and local health departments can augment these recommendations by highlighting the benefits of team-based care and supporting health systems and organizations with implementation.
Rapid Evaluations of Telehealth Strategies to Address Hypertension: Public health professionals and clinicians can learn from these rapid evaluations of two Federally Qualified Health Centers, both of which incorporated telehealth in their practices. Telehealth is a promising health care strategy that also raises a new set of access barriers.
This page was last updated on this date. Updates may include minor edits, image changes, or other modifications to page content.
The information on this page was last reviewed by subject matter experts to ensure accuracy.
- Koonin LM, Hoots B, Tsang CA, et al. Trends in the use of telehealth during the emergence of the COVID-19 pandemic—United States, January–March 2020. MMWR Morb Mortal Wkly Rep. 2020;69(43):1595–1599.
- Demeke HB, Merali S, Marks S, et al. Trends in use of telehealth among health centers during the COVID-19 pandemic—United States, June 26–November 6, 2020. MMWR Morb Mortal Wkly Rep. 2021;70(7):240–244.
- Virani SS, Alonso A, Aparicio HJ, et al. Heart disease and stroke statistics—2021 update: a report from the American Heart Association. Circulation. 2021;143(8):e254–e743.