


Key points
- Initial diagnosis of infant botulism is based on clinical symptoms.
- Clinical consultation is available for suspected cases.
- If clinical consultation supports infant botulism, begin treatment as soon as possible. Do not wait for laboratory confirmation.
- Infant botulism is a notifiable disease. All suspected cases must be reported to the state public health department.
Overview
Infant botulism is an intestinal toxemia.
The disease occurs after spores of the bacterium Clostridium botulinum or related species are swallowed. These spores temporarily colonize an infant's large intestine and produce botulinum neurotoxin.
The neurotoxin binds to cholinergic nerve terminals and cleaves intracellular proteins necessary for acetylcholine release. This can result in:
- Bulbar palsies
- Hypotonia
- A symmetric, descending, flaccid paralysis
Signs and symptoms

Patients with infant botulism may present with some or all the following signs and symptoms:
- Constipation
- Poor feeding
- Weak and altered cry
- Hypotonia or paralysis
- Ptosis (drooping eyelid)
- Sluggish pupils
- Flat facial expression
- Diminished suck and gag reflexes
- Respiratory difficulty and possibly respiratory arrest
Diagnosis
The hallmark of infant botulism is progressive muscle weakness, beginning with muscles controlled by the cranial nerves.
Suspicion for infant botulism increases with
- Loss of pupillary light reflex (especially a light reflex that fatigues after multiple repetitions)
- Normal neuroimaging
- Negative laboratory test results for other infectious diseases
Infant botulism is frequently misdiagnosed. Its signs and symptoms can resemble Guillain-Barré syndrome, spinal muscular atrophy, sepsis, some infectious diseases, and other neurologic or metabolic disorders.
If uncertain about the diagnosis, observe the patient daily (inpatient or outpatient) and consider consulting pediatric infectious disease or pediatric neurology specialists.
Steps to take
Case consultation
If you suspect your infant patient has botulism, immediately call 510-231-7600 for case consultation. Consultation is available 24/7.
- You will reach the on-call physician at the Infant Botulism Treatment and Prevention Program (IBTPP) at the California Department of Public Health.
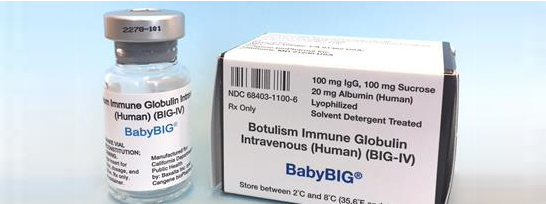
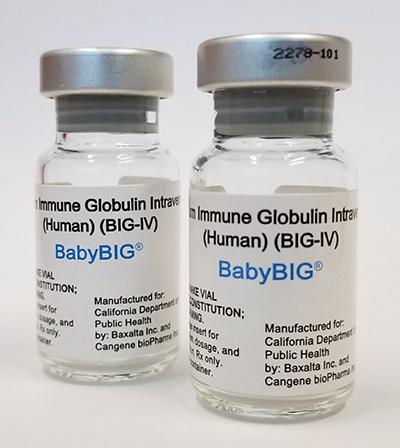
- The physician will provide a no-cost clinical consultation and release BabyBIG® treatment if the patient's clinical findings indicate infant botulism.
Case reporting
After consulting with IBTPP, call your state health department to:
- Receive guidance on specimen collection, storage, and submission (also refer to the IBTPP collection guidance)
- Ask questions about testing methods
- Learn about mandatory reporting
If clinical consultation supports infant botulism, begin treatment with BabyBIG® as soon as it is available. The recommended total dosage of BabyBIG® is now 0.4 mL/kg (20 mg/kg), given as a single intravenous infusion.
Keep in mind, initial diagnosis is based on clinical symptoms. Do not wait for laboratory confirmation to begin treatment.
A stool or enema specimen is required for definitive diagnosis of infant botulism. Enemas should be performed with sterile, non-bacteriostatic water.
Diagnostic testing is done through your state public health department laboratory. CDC provides testing services for some state public health departments.
This specialized testing often takes days to complete. Follow up with your state health department if you do not receive results within five days.
Infant botulism is a notifiable disease in the United States.
Physicians must promptly notify the state health department of suspected cases. As a courtesy, the Infant Botulism Treatment and Prevention Program (IBTPP) at the California Department of Public Health notifies the state health department after BabyBIG® infusion is completed. Laboratories must notify the state health department of all confirmed cases.
State health departments report confirmed cases to CDC through the National Notifiable Diseases Surveillance System.
This page was last updated on this date. Updates may include minor edits, image changes, or other modifications to page content.
The information on this page was last reviewed by subject matter experts to ensure accuracy.
- Photos are courtesy of the California Department of Public Health.